
Fitness 18 min read
India Has the World’s 2nd-Highest Childhood Obesity Rate. Here’s Why
India has 41 million children aged 5–19 living with overweight or obesity.[1] On World Obesity Day 2026, the World Obesity Federation confirmed a major concern. India now ranks…
Reading about body composition? Find an InBody test centre near you →
India has 41 million children aged 5–19 living with overweight or obesity.[1] On World Obesity Day 2026, the World Obesity Federation confirmed a major concern. India now ranks second in the world, behind only China, in total childhood obesity burden.
However, many of these children may not be flagged by standard growth charts alone. Many parents simply see a healthy, well-fed child. At the same time, many clinicians rely mainly on BMI. Because of this, deeper health risks can be missed. These include high visceral fat, low skeletal muscle, and hidden metabolic issues. All of this can exist behind a “normal” number.
In this article, we examine the seven root causes of childhood obesity in India. We also explain why body composition analysis can give more detail than BMI. In fact, it is one of the few tools that can help flag these risks early in an outpatient setting.
| 41 Million Indian children (5–19 yrs) overweight or obese in 2025[1] | #2 Globally India’s rank, behind only China (62M)[1] | 4.8% / year Annual rise in the prevalence of overweight and obesity in Indian children (2010–25)[1] | 56 Million Projected affected Indian children by 2040[1] |
Why India? Understanding the Scale of the Crisis
The World Obesity Atlas 2026, released on World Obesity Day, March 4, 2026, confirmed that approximately 41 million Indian children aged 5–19 are living with overweight or obesity. Of these, 14 million are classified as living with obesity specifically. India sits second only to China (62 million) and well ahead of the United States (27 million).[1]
What makes India’s position especially alarming is the rate of acceleration. The prevalence of overweight and obesity among Indian children has been rising by about 4.8% per year (compound annual growth, 2010–2025), one of the ten fastest rates globally.[1] Without intervention, the World Obesity Atlas 2026 projects about 56 million overweight and obese Indian children by 2040.[1] That brings with it a projected surge in paediatric hypertension, hyperglycaemia, and metabolic liver disease that India’s health system will struggle to absorb.
BY 2040, WITHOUT INTERVENTION
BMI-related hypertension in Indian children will rise from 2.99 million → 4.21 million cases. Hyperglycaemia will increase from 1.39 million → 1.91 million. High triglycerides will jump from 4.39 million → 6.07 million.
Source: World Obesity Atlas 2026.[1]

Reason 1: The Rapid Urbanisation–Diet Transition Trap
India’s economic growth has transformed the dietary landscape, but not in a healthy direction. Retail sales of ultra-processed food (UPF) in India surged from about USD 0.9 billion in 2006 to nearly USD 38 billion in 2019, a roughly 40-fold rise, according to India’s Economic Survey 2025–26.[2] The Economic Survey 2024–25, citing WHO India data, reported that retail sales of ultra-processed foods grew at a CAGR of 13.7% between 2011 and 2021.[3]
The shift from traditional fibre-rich diets to calorie-dense, nutrient-poor packaged foods may be particularly damaging in children, whose eating habits and metabolism are still developing. The ICMR-NIN Dietary Guidelines for Indians 2024 estimate that unhealthy diets account for 56.4% of India’s total disease burden.[4] Furthermore, marketing of ultra-processed, energy-dense foods to children is expanding, particularly through digital channels.[5]
CLINICAL IMPLICATION
Children from urban semi-affluent households may warrant early metabolic screening regardless of BMI percentile. South Asian children and adolescents appear to face higher cardiometabolic risk at lower BMI than children of other ancestries.[6] InBody body composition analysis is one of the tools that can help estimate visceral fat in the consultation room, in under 60 seconds.

Reason 2: Catastrophically Low Physical Activity Levels
The World Obesity Atlas 2026 reports that 74% of Indian adolescents aged 11–17 fail to meet the WHO-recommended average of 60 minutes of moderate-to-vigorous physical activity per day.[1][7] This is close to the global picture: an estimated 81% of school-going adolescents worldwide were insufficiently active in 2016.[8]
The likely causes are layered: academic pressure compressing recreational time, the explosion of screen-based entertainment replacing outdoor play, urban infrastructure lacking safe outdoor spaces, and cultural norms deprioritising physical activity, particularly for girls. Sedentary behaviour during childhood can affect not just caloric balance but also the development of insulin sensitivity, skeletal muscle mass, and basal metabolic rate.
This can create a metabolic phenotype that clinicians describe as ‘normal weight obesity’, the thin-fat syndrome. A child presenting at BMI 19 kg/m² may carry clinically significant visceral fat, elevated liver enzymes, and skeletal muscle mass well below the population norm. BMI will not flag any of this.
The ‘Thin-Fat Indian Child’ Paradox
Reviews of South Asian children and adolescents suggest they face higher cardiometabolic risk at lower BMI values than children of other ancestries, and body composition is one proposed contributor.[6] A child at 19 kg/m² may carry clinically significant visceral fat and elevated liver enzymes. Because BMI cut-offs derived from other populations may under-call risk in South Asian children, and because Indian meta-analyses suggest national estimates such as the Atlas may be an underestimate,[9] the 41 million figure may be conservative.
KEY INSIGHT FOR CLINICIANS
The 2015 IAP BMI charts use lower adult-equivalent cut-offs, 23 kg/m² for overweight and 27 kg/m² for obesity, because Asians are known to have more adiposity and cardiometabolic risk at a lower BMI.[10] IAP recommends its 2015 charts for assessing Indian children aged 5–18 years, and its 2023 guideline uses BMI on these charts as the basis for diagnosis.[11] For patients near these thresholds, body composition analysis can be a useful next step. Learn more about visceral fat in Indian patients.
Reason 3: Suboptimal Early Nutrition and Breastfeeding Deficits
The nutritional programming hypothesis that early-life metabolic exposure shapes lifelong disease risk is increasingly supported by evidence. The World Obesity Atlas 2026 gives India a summary exposure value (a risk-weighted exposure score, not a simple percentage of infants) of 32.6% for sub-optimal breastfeeding in infants aged 1–5 months.[1] WHO recommends exclusive breastfeeding for the first six months of life,[12] and a meta-analysis found that people who were breastfed had lower odds of later overweight or obesity (pooled odds ratio 0.74, or 0.87 in high-quality studies).[13]
Complementary feeding practices can compound the risk further, since early introduction of high-sugar, low-fibre weaning foods may add to it. India’s CNNS 2016–18 found a significantly higher prevalence of obesity among children and adolescents in higher wealth quintiles and in urban areas,[14] so overnutrition risk may be concentrated in families that clinicians do not expect to flag.
- Higher maternal pre-pregnancy BMI and gestational weight gain above recommendations are each associated with a higher risk of childhood overweight and obesity[15]
- In CNNS 2016–18, obesity prevalence among children and adolescents was significantly higher in higher wealth quintiles and among urban residents[14]
Reason 4: Maternal Metabolic Health and the Intergenerational Transmission Risk
Childhood obesity in India is not only a childhood problem, but it is also an intergenerational one. The World Obesity Atlas 2026 gives India a summary exposure value (a risk-weighted score) of 13.4% for high BMI among women of reproductive age (15–49), and reports that 4.2% of these women live with Type 2 diabetes.[1] Higher maternal BMI is associated with a higher risk of overweight and obesity in children across early, mid and late childhood.[15]
Maternal obesity is thought to increase fetal fat deposition through hyperinsulinaemia and hyperleptinaemia in utero. Gestational diabetes mellitus (GDM) is common in India: a 2024 meta-analysis pooled a prevalence of 13% (95% CI 9–16%),[16] while the national ICMR-INDIAB study estimated 22.4% using NICE criteria.[17] GDM exposes the fetus to hyperglycaemia, which is thought to programme insulin resistance that can later show up as excess adiposity in childhood.
Fetal Origins of Adult Disease: The Indian Context
The Developmental Origins of Health and Disease (DOHaD) framework is especially relevant in India, where the juxtaposition of maternal undernutrition and overnutrition creates a complex metabolic milieu. The ‘thin-fat’ phenotype at birth, low birth weight with relatively preserved body fat, has been documented in rural Indian newborns in the Pune Maternal Nutrition Study,[18] and may predispose to early visceral adiposity when exposed to a post-natal calorie-surplus environment. It is a metabolic vulnerability that BMI alone detects poorly.
CLINICAL PEARL
Clinicians may consider screening children of mothers with T2DM, GDM history, or BMI >23 kg/m² for early metabolic risk markers (fasting insulin, HOMA-IR, and waist-to-height ratio) from age 6 onwards, irrespective of their absolute BMI percentile. This is a practical suggestion rather than a published guideline recommendation. InBody body composition scanning can be included in this workup.
Reason 5: The Double Burden: Undernutrition and Overnutrition Coexist
India is one of several large countries where a clinician can encounter moderate acute malnutrition and Grade II obesity in the same classroom, the same family, and sometimes through intergenerational paradox in different children of the same mother.[4] UNICEF’s Child Nutrition Report 2025 found that, for the first time globally, the prevalence of obesity among children and adolescents aged 5–19 (9.4%) has surpassed that of underweight (9.2%).[5]
India exemplifies this double burden of malnutrition, a simultaneous public health crisis that profoundly complicates both clinical and policy responses. A systematic review of Indian studies found that overweight and obesity were rising not only among higher socio-economic groups but also among lower-income groups, where underweight remains a major concern.[19] Programmes historically designed to address undernutrition, including ICDS and PM-POSHAN, now operate in a nutritional landscape where their supplementary caloric provisions may paradoxically accelerate overnutrition in certain subpopulations. Reforming these programmes to provide nutritionally complete rather than merely calorie-adequate interventions is a recognised and urgent gap.

Reason 6: Inadequate School Nutrition and Obesogenic Food Environments
The World Obesity Atlas 2026 estimates that only 35.5% of school-age children in India receive school meals (India’s national scheme is PM-POSHAN, formerly the Mid-Day Meal Scheme), and its policy scorecard lists India as having no obesity goals within school food provision.[1] More critically, the food environment surrounding Indian schools may be increasingly obesogenic.
A mixed-methods study of nine schools in Delhi and the National Capital Region found that the food and drink options in and around them were largely high in fat, salt and sugar, with vendors operating outside school gates at dispersal time.[20] Older children with pocket money and reduced parental supervision can make independent food purchases several times a day.
Screen Time as a Dual-Channel Obesity Driver
Excess screen time is associated with childhood obesity, plausibly through two pathways: (1) displacement of physical activity, and (2) exposure to digital marketing of energy-dense foods that can shape food preferences. A 2023 Indian meta-analysis of 186,901 children aged 3–18 (21 studies) found a pooled obesity prevalence of 8.4% and overweight prevalence of 12.4%,[21] and a 2024 editorial noted that these rates are higher than World Obesity Atlas figures, suggesting the Atlas may understate the true burden.[9]
- In India’s national nutrition survey (CNNS 2016–18), screen time was associated with higher odds of overweight and obesity among adolescents (adjusted odds ratio 1.63, 95% CI 1.22–2.19)[14]
- In the Delhi-NCR school study, students at all six private schools were exposed to advertisements for foods and drinks high in fat, salt or sugar around their school[20]

Reason 7: A Healthcare System Not Yet Calibrated for Paediatric Obesity
India’s primary healthcare infrastructure has traditionally been configured to detect and treat undernutrition and acute infectious disease in children. Systematic BMI screening, waist circumference measurement, and metabolic risk stratification during well-child visits may not yet be routine in many PHC and community health facilities.
The Atlas estimates that India’s prevalence of overweight and obesity among children aged 5–19 has risen by about 4.8% a year since 2010, and that 181 countries missed the global target to halt the rise in adolescent obesity by 2025.[1] Paediatric obesity in India can also be framed by caregivers, and sometimes by clinicians, as a sign of prosperity rather than a medical condition requiring intervention. This normalisation may delay presentation.
The clinical consequences of delayed detection can be serious. A 2024 Indian Journal of Endocrinology and Metabolism editorial notes that children with obesity are at higher risk of chronic conditions such as type 2 diabetes, hypertension and cardiovascular disease,[9] and the Indian Academy of Pediatrics’ 2023 guideline recommends evaluating all children over ten years old with obesity for hypertension, dyslipidaemia, hyperglycaemia and non-alcoholic fatty liver disease (NAFLD/MASLD).[11]
What Does Timely Clinical Intervention Involve?
The Indian Academy of Pediatrics’ 2023 guideline identifies healthy diet practices, daily moderate-to-vigorous physical activity and reduced screen time as the mainstay of prevention and management of childhood obesity.[11] Tracking body composition alongside weight and BMI can help families and clinicians see whether such a programme is changing fat and muscle.
A CRITICAL DIAGNOSTIC GAP
InBody bioelectrical impedance analysis can help clinicians flag high visceral fat and skeletal muscle deficits even in children with ‘normal’ BMI, the thin-fat phenotype that BMI alone can miss. Body composition analysis can complement, but does not replace, BMI and waist circumference, which remain the basis of IAP’s 2023 guidance.[11] An InBody scan takes under 60 seconds and delivers results immediately.
BMI vs Body Composition Analysis: Why It Matters for Indian Children
The index behind BMI was described by Adolphe Quetelet in the 1830s as a population-statistics tool, not as a clinical measure of individual metabolic health.[22] It uses only weight and height, cannot distinguish fat from muscle, and standard international cut-offs have no ethnic correction for South Asians, who can develop metabolic disease at BMI levels Western guidelines classify as healthy.[23] Furthermore, it cannot detect visceral fat, skeletal muscle deficit, or early metabolic deterioration.
Body composition analysis with InBody measures several markers BMI completely ignores — each one critical for Indian children presenting in your clinic today.
| What You Need to Know | BMI | InBody Body Composition |
|---|---|---|
| Is this child carrying excess fat? | Partial weight only, no fat detail | Yes, an estimate of body fat % |
| Is skeletal muscle mass adequate? | No, cannot measure muscle at all | Yes, skeletal muscle mass in kg vs population norm |
| Is visceral fat at dangerous levels? | No, completely invisible to BMI | Yes, Visceral Fat Level on a 1–20 scale |
| Is the thin-fat phenotype present? | No, will show “normal” | Yes, detects high fat and low muscle simultaneously |
| Is there fluid imbalance or possible inflammation? | No | Partly, the ECW/TBW ratio can flag fluid imbalance |
| Does it account for Indian ethnicity? | No, uses Western population norms | Yes, Asian-specific reference values applied |
| Can it track the impact of intervention? | Unreliable muscle gain raises BMI | Yes, tracks fat loss and muscle gain independently |
Real Case: The Child Who Was ‘Normal’ on Paper
A 13-year-old boy from a middle-class household in Pune was brought to a paediatric endocrinology clinic for a routine health check. His BMI was 21.3, which is below the IAP 2015 obesity cut-off for a 13-year-old boy (23.4 kg/m²) but just above its overweight line (20.2 kg/m²).[10] His parents had no concerns. Nevertheless, his fasting glucose was borderline, and he complained of persistent fatigue and poor concentration at school.
His InBody scan told a different story. It revealed a Visceral Fat Level of 10 (approaching high risk), a Body Fat Percentage of 29.4%, and Skeletal Muscle Mass 2.1 kg below norm for his height and age. He was a textbook presentation of the thin-fat Indian phenotype, and his BMI alone could not show it.
After a 12-week programme of structured daily physical activity (60 minutes, mixed aerobic and resistance), reduced ultra-processed snack consumption, and increased dietary protein, his follow-up InBody scan showed measurable improvement across every metabolic marker. His BMI had moved by less than 0.4 units over the same period, a number that would have told his clinician nothing had changed.
| ↓2 units Visceral Fat Level reduction | +1.6 kg Skeletal Muscle Mass gained | ↓4.1% Body Fat Percentage reduction | Normal Fasting glucose at 12 weeks |
Which Children Should Be Screened for Obesity in India?
Body composition screening may be relevant for a broader group of Indian children than standard BMI criteria suggest. In particular, the following groups may benefit from early InBody assessment:
- Children of mothers with T2DM, GDM history, or BMI >23 kg/m²: Intergenerational metabolic risk may warrant screening from age 6, regardless of the child’s current BMI
- Children with normal BMI but borderline blood glucose, elevated liver enzymes, or persistent fatigue: The thin-fat phenotype can be one underlying cause and is difficult to detect without body composition analysis
- Urban children aged 8–15: A group in which UPF consumption, screen time, and physical inactivity often converge
- Children on supervised weight or fitness programmes: InBody tracks fat loss and muscle gain independently, providing the clinically meaningful feedback that BMI cannot deliver
- Children with PCOS, prediabetes, or incidental fatty liver on imaging: Body composition data can help inform treatment intensity and targets
- Children over 10 with sedentary academic lifestyles: Early sarcopenic obesity, high fat combined with low muscle, can be missed by standard clinical screening
Frequently Asked Questions
Q. What is the current childhood obesity rate in India?
As of 2025, the World Obesity Atlas 2026 estimates approximately 41 million Indian children aged 5–19 have high BMI, including 14 million classified as living with obesity specifically. India ranks second globally after China (62 million).[1] IAP-adjusted BMI cut-offs (adult-equivalent 23 and 27 kg/m²) are lower than the conventional adult 25 and 30,[10] and Indian meta-analyses suggest the Atlas may understate prevalence, so the true burden may be higher.[9]
Q. Which age group is most affected by childhood obesity in India?
Adolescents aged 10–19 are most heavily affected, with more than 26 million classified as overweight or obese in 2025. However, the 5–9 age group accounts for nearly 14.9 million affected children,[1] signalling early onset of adiposity that is associated with early nutrition, screen time, and inactivity from primary school age onwards.
Q. What diseases are linked to childhood obesity in India?
Childhood obesity in India is linked to a higher risk of type 2 diabetes mellitus, hypertension, dyslipidaemia (particularly high triglycerides), metabolic-associated steatotic liver disease (MASLD/NAFLD), and cardiovascular disease.[9][11] By 2040, BMI-attributed hypertension in Indian children is projected to rise to 4.21 million cases, hyperglycaemia to 1.91 million, and fatty liver disease (MASLD) to 11.9 million.[1]
Q. What are the most effective interventions for childhood obesity in India?
A multi-pronged approach is recommended: an average of 60 minutes of daily moderate-to-vigorous physical activity,[7] healthy diet practices and reduced screen time,[11] and exclusive breastfeeding for the first 6 months.[12] Wider measures such as restricting ultra-processed food consumption, school-based nutrition education, regulation of digital food marketing to children, and family-based behavioural support are also commonly proposed. Regular InBody body composition scanning allows clinicians and families to track fat loss, muscle gain, and visceral fat change objectively throughout the intervention — providing the motivational data that BMI or weight alone cannot.
Key Takeaways
- India has 41 million children living with overweight or obesity, the world’s second-highest burden after China, with prevalence rising about 4.8% per year since 2010.[1]
- The 7 root causes: diet transition, physical inactivity, early nutrition deficits, maternal metabolic health, the double burden, school food environments, and healthcare system gaps interact as a system, not in isolation.
- BMI alone can underestimate risk in Indian children because of the thin-fat phenotype. IAP recommends its 2015 BMI charts, which use lower adult-equivalent cut-offs (23 and 27 kg/m²), for children aged 5–18.[10]
- InBody body composition analysis estimates visceral fat, skeletal muscle mass, and body fat percentage in under 60 seconds, providing data that BMI cannot at the point of care.
- Structured lifestyle intervention (healthy diet, daily physical activity and less screen time) is the mainstay of management in IAP’s 2023 guideline.[11] Body composition scanning can help track changes in fat and muscle alongside BMI.
- Without decisive action, about 56 million Indian children are projected to be overweight or obese by 2040,[1] with downstream consequences for India’s diabetes, cardiovascular disease, and liver disease burden for decades to come.
See What Your Child’s Body Is Really Made Of
An InBody scan takes under 60 seconds and gives clinicians the body composition data needed to detect childhood obesity risk that BMI cannot show, including visceral fat level, skeletal muscle deficit, and body fat percentage, all measured against Asian-specific reference values.
Find an InBody Scanner Near You
References
- World Obesity Federation. World Obesity Atlas 2026: Childhood Obesity (2nd edition). London: World Obesity Federation; released 4 March 2026. India country profile (p. 153), Table 1.1 and Table 1.3. Publication page · PDF
- Ministry of Finance, Government of India. Economic Survey 2025-26, Chapter 11 (Education and Health: What Works and What’s Next), para 11.46. Government of India
- Ministry of Finance, Government of India. Economic Survey 2024-25, Chapter 11 (Social Sector: Extending Reach and Driving Empowerment), citing WHO India (2023), The growth of ultra-processed foods in India. Government of India
- ICMR-National Institute of Nutrition. Dietary Guidelines for Indians – 2024. Hyderabad: ICMR-NIN; 2024. ICMR-NIN (PDF)
- UNICEF. Feeding Profit: How food environments are failing children. Child Nutrition Report 2025. New York: UNICEF; September 2025. UNICEF
- Wolf RM, Nagpal M, Magge SN. Diabetes and cardiometabolic risk in South Asian youth: a review. Pediatr Diabetes. 2021;22(1):52-66. PubMed · DOI
- Bull FC, Al-Ansari SS, Biddle S, et al. World Health Organization 2020 guidelines on physical activity and sedentary behaviour. Br J Sports Med. 2020;54(24):1451-1462. PubMed · DOI
- Guthold R, Stevens GA, Riley LM, Bull FC. Global trends in insufficient physical activity among adolescents: a pooled analysis of 298 population-based surveys with 1.6 million participants. Lancet Child Adolesc Health. 2020;4(1):23-35. PubMed · DOI
- Jacob JJ. Tackling the Rising Tide: Understanding the Prevalence of Childhood Obesity in India (editorial). Indian J Endocrinol Metab. 2024;28(2):101-103. PubMed · DOI
- Indian Academy of Pediatrics Growth Charts Committee, Khadilkar V, Yadav S, et al. Revised IAP growth charts for height, weight and body mass index for 5- to 18-year-old Indian children. Indian Pediatr. 2015;52(1):47-55. PubMed · DOI
- Khadilkar V, Shah N, Harish R, et al. Indian Academy of Pediatrics revised guidelines on evaluation, prevention and management of childhood obesity. Indian Pediatr. 2023;60(12):1013-1031. PubMed · DOI
- World Health Organization. Infant and young child feeding (fact sheet, updated 4 August 2026). WHO
- Horta BL, Loret de Mola C, Victora CG. Long-term consequences of breastfeeding on cholesterol, obesity, systolic blood pressure and type 2 diabetes: a systematic review and meta-analysis. Acta Paediatr. 2015;104(467):30-37. PubMed · DOI
- Sethi V, Bassi S, Bahl D, et al. Prevalence of overweight and obesity and associated demographic and health factors in India: findings from Comprehensive National Nutrition Survey (CNNS). Pediatr Obes. 2024;19(4):e13092. PubMed · DOI
- Voerman E, Santos S, Patro Golab B, et al. Maternal body mass index, gestational weight gain, and the risk of overweight and obesity across childhood: an individual participant data meta-analysis. PLoS Med. 2019;16(2):e1002744. PubMed · DOI (cohorts from Europe, North America and Australia)
- Mantri N, Goel AD, Patel M, et al. National and regional prevalence of gestational diabetes mellitus in India: a systematic review and meta-analysis. BMC Public Health. 2024;24:527. PubMed · DOI
- Mohan V, Deepa M, Tandon N, et al. Prevalence of gestational diabetes mellitus in India: the ICMR-INDIAB national study (ICMR-INDIAB-24). Indian J Med Res. 2025;162(4):460-469. PubMed · DOI
- Yajnik CS, Fall CH, Coyaji KJ, et al. Neonatal anthropometry: the thin-fat Indian baby. The Pune Maternal Nutrition Study. Int J Obes Relat Metab Disord. 2003;27(2):173-180. PubMed
- Ranjani H, Mehreen TS, Pradeepa R, et al. Epidemiology of childhood overweight & obesity in India: a systematic review. Indian J Med Res. 2016;143(2):160-174. PubMed · DOI
- Bassi S, Bahl D, Arora M, Tullu FT, Dudeja S, Gupta R. Food environment in and around schools and colleges of Delhi and National Capital Region (NCR) in India. BMC Public Health. 2021;21:1767. PubMed · DOI
- Singh S, Awasthi S, Kapoor V, Mishra P. Childhood obesity in India: a two-decade meta-analysis of prevalence and socioeconomic correlates. Clin Epidemiol Glob Health. 2023;23:101390. DOI
- Eknoyan G. Adolphe Quetelet (1796-1874): the average man and indices of obesity. Nephrol Dial Transplant. 2008;23(1):47-51. PubMed · DOI
- WHO Expert Consultation. Appropriate body-mass index for Asian populations and its implications for policy and intervention strategies. Lancet. 2004;363(9403):157-163. PubMed · DOI

Most trending articles

Creatine and Your Body Composition Scan: What Changes
Creatine raises body water and lean mass readings within a week on BIA and DXA. What the studies show and how to time your scans to read progress honestly.

Fitness Testing and Body Composition for Sports Academies
A practical fitness testing battery for Indian sports academies: body composition, grip, jumps, sprints, Yo-Yo, Khelo India context and youth maturation.
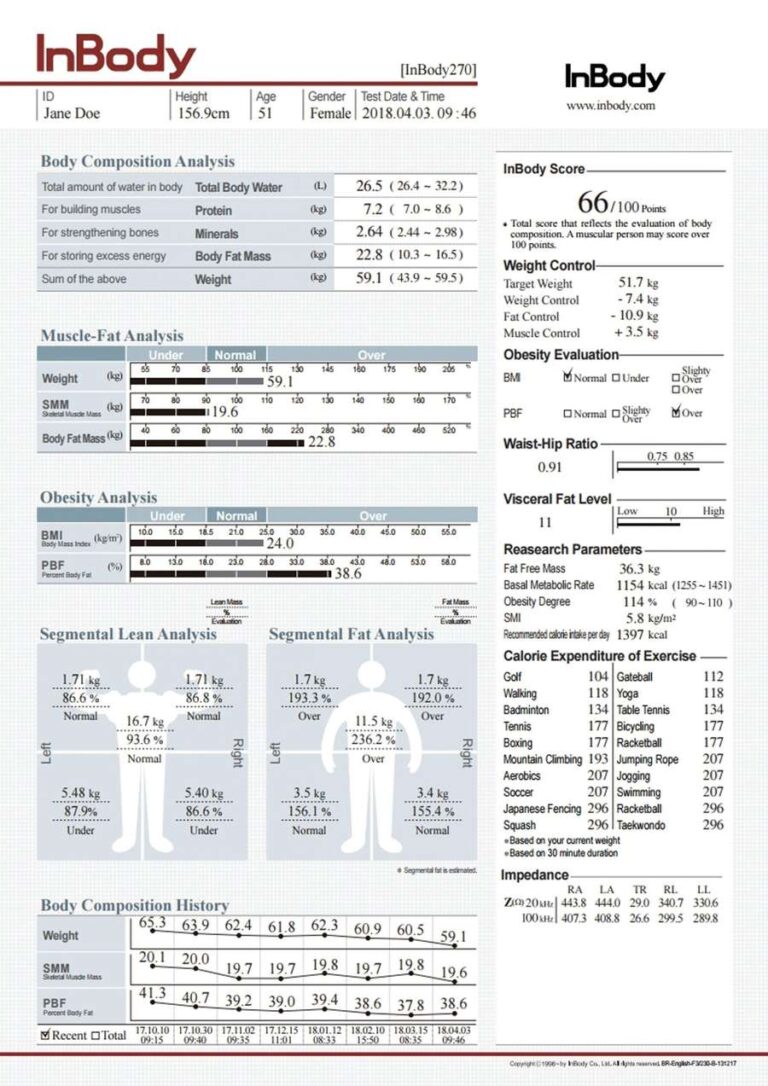
Skeletal Muscle Mass (SMM): Normal Range on InBody
What SMM means on your InBody report, how the 90-110% normal bar works, why SMM is not SMI, and the AWGS cut-offs used to screen for low muscle.